
Healthcare marketing · Patient communication · Cash-pay value
Concierge Care Marketing: Communicating the Value of Personalized, Cash-Pay Care

Quick answer: how should personalized, cash-pay care be marketed?
Concierge care marketing should explain the actual care model, included services, fees, insurance relationship, and access arrangements before asking a patient to book. Use verified provider information and a clear inquiry path. Describe personalized service in specific, supportable terms; paying more or joining a membership does not guarantee better clinical outcomes. Effective messaging helps people understand the offer and decide whether it fits their needs.
A prospective patient may appreciate personalized attention yet still hesitate over a cash-pay service. What does the fee include? Does the practice bill insurance? Who answers questions? Is an initial consultation a treatment appointment, a membership discussion, or an evaluation? A beautiful website cannot resolve those questions if its wording remains vague.
Concierge care marketing turns a service promise into understandable information. It connects the experience a practice can actually deliver with the details a person needs before making a decision. The task is to communicate value without making access sound unlimited, costs sound all-inclusive, or medical results sound assured.
This guide is for practice owners, managers, and healthcare marketing teams. It covers personalized cash-pay services, membership messaging, transparent costs, patient expectations, website structure, and qualified inquiry measurement. Best Edge Medical Marketing is a marketing agency, not the provider of clinical services described in these planning examples.
What patients receive
Define the service, the provider’s role, what is included, and what requires a separate arrangement.
What patients commit to
Make fees, billing terms, insurance arrangements, and any membership conditions easy to understand.
What patients can expect
Describe contact channels, scheduling, response arrangements, and the next step accurately.
What is concierge care marketing?
Concierge care marketing is the process of explaining a practice’s personalized service model so people can understand its scope, costs, access, and consultation process. It may support a formal concierge membership, a defined cash-pay service, or another arrangement. The website should describe the actual offer rather than assume that everyone interprets “concierge” the same way.
Concierge-level service is a description of the experience. A concierge membership is a particular contractual or payment arrangement. A practice may offer attentive coordination without charging a recurring retainer. Another may collect a membership fee while billing separately for certain services. Those differences should be visible before a patient provides payment or commits to enrollment.
Start by documenting the service as operations delivers it: who provides care, where visits occur, how requests are handled, and what fees apply. If the marketing team cannot explain those details consistently, the positioning is not ready. A slogan about personalized attention cannot substitute for a defined service.
The commercial goal is to attract informed inquiries and reduce preventable confusion. The clinical goal remains appropriate care determined by qualified professionals. A person who understands the offer and decides it does not fit has still received useful information. Persuading everyone to join is not a sensible measure of truthful healthcare communication.
How do concierge-level service, concierge medicine, and direct primary care differ?
The differences depend on the care scope, contract, and payment process—not the word “personalized.” Explain the model plainly before describing convenience or amenities. The American Academy of Family Physicians describes direct primary care as periodic direct payments for a defined set of primary care services, typically replacing third-party billing for those contracted services.
| Model | What the label may describe | What must be clarified |
|---|---|---|
| Concierge-level service | A personalized experience, communication, or coordination approach. | The actual service and fee structure; membership should not be implied unless it exists. |
| Concierge medicine | A retainer or membership arrangement with defined services or amenities. | The agreement, included benefits, exclusions, and any separate medical-service billing. |
| Direct primary care | A direct-payment contract for a defined primary care scope. | Covered services, limits, and care outside the contract. |
| Visit-based cash-pay care | Payment for a visit, evaluation, or specified service. | What the payment buys and which follow-up or additional services cost extra. |
| Hybrid arrangement | A combination of membership, visit fees, or insurance billing. | Which payment rules apply to which services and patients. |
This comparison is a communication framework, not a determination of a practice’s legal or insurance status. Model names are used differently across the market. An owner’s preferred branding does not override the actual agreement, professional obligations, or payer rules.
Explain services beyond the practice’s scope as well. A primary care membership should not be presented as covering every specialist, hospital service, or emergency expense. Patients need to understand how other care is arranged and paid for, including whether separate coverage remains important for their circumstances.
What do patients need to understand before deciding?
Patients need an understandable answer to what changes, what it costs, and whether the arrangement fits their needs. They may compare the offer with their existing clinician, an insurance-based practice, a visit-based service, or delaying a nonurgent decision. Marketing should help that comparison rather than treat every objection as resistance to overcome.
A useful explanation addresses practical questions: who they will see, whether visits happen in person, how follow-up works, and how records or referrals are handled. Identify which elements are included and which depend on clinical assessment or a separate provider. Do not allow “coordinated care” to imply that the practice controls external appointment availability.
Financial fit matters too. People may need time to understand recurring charges, consider household expenses, or compare alternatives. Presenting reasonable questions about cost as a lack of commitment can damage trust. A respectful inquiry process should allow questions and a voluntary decision without pressure to purchase treatment.
Describe the audience through relevant needs rather than assumptions about wealth. A busy schedule, uncertainty about billing, or a desire for clear communication can affect people in many circumstances. Discuss the services available and the limits honestly. A healthcare offer should not imply that patients who pay less are less deserving of attentive, evidence-based care.
How can practices communicate value without relying on vague premium language?
Connect each genuine service feature to a practical patient question, then explain its boundaries. “Personalized,” “comprehensive,” and “premium” can introduce the positioning, but they do not tell someone what to expect. Specific information gives the message substance and makes it easier for staff to repeat accurately.
| Broad message | Details to explain | Boundary to preserve |
|---|---|---|
| Personalized attention | Who reviews needs, how the initial visit works, and what follow-up is offered. | Do not imply that every requested test or treatment will be appropriate. |
| Convenient access | Contact channels, scheduling process, and response arrangements. | Do not imply continuous availability or emergency services unless accurately defined. |
| Care coordination | What records, referrals, or communication the team helps manage. | Identify services and decisions controlled by outside providers. |
| Transparent pricing | The fee basis, inclusions, exclusions, and how current costs are obtained. | Do not present a starting price as the total cost of all potential care. |
A strong value statement has three parts: the specific service, the practical experience it supports, and the conditions under which it applies. That structure can guide website sections, brochures, inquiry scripts, and onboarding materials without adding an unsupported clinical promise.
For example, if a practice genuinely offers a scheduled introductory discussion, explain what the discussion covers and whether it is clinical. A patient should not mistake a service-model conversation for an examination or assume it establishes treatment eligibility. Clarity protects both the value proposition and the person’s expectations.
Ask staff to explain the offer using the same core facts. If the website says one thing and the front desk describes another, additional advertising increases the inconsistency. Resolve the underlying service definition before polishing the headline.
How should fees, exclusions, and insurance arrangements be explained?
Explain the payment structure where people evaluate the service, with a clear route to current, individualized cost information. State whether the arrangement involves a visit fee, recurring membership, enrollment charge, or another structure. Do not bury the existence of a required fee behind reassuring language about convenience.
- Fee basis: what is charged, when payment is due, and whether charges recur.
- Included scope: which visits, services, or amenities the fee covers.
- Separate charges: which tests, procedures, outside services, or follow-up arrangements may cost extra.
- Insurance relationship: whether the practice bills insurance, what that means for the particular service, and who can answer coverage questions.
- Agreement terms: relevant renewal, cancellation, refund, and change conditions if a membership exists.
Coverage should not be guessed from a broad label. Medicare states that it does not cover concierge membership fees and describes rules affecting participating physicians and covered services. Do not turn that into a universal statement about every insurance arrangement or every item a practice provides. Billing and coverage wording should be verified for the actual model.
Cost transparency also includes an appropriate estimate process. CMS explains good faith estimates for uninsured or self-pay care, including requests and qualifying advance scheduling. A general website price list is not automatically a substitute for a required estimate. The practice should confirm which requirements apply to its services and operational process.
If fees vary after assessment, explain why and how the patient receives relevant information before agreeing to the service. Avoid inventing universal price ranges or presenting an illustrative example as a quote. An agency should use verified practice information rather than fill missing pricing details with an industry average.
Practical test: could a patient distinguish the initial payment from potential additional charges after reading the service page? If not, the pricing explanation needs more work.
How can a practice describe access without overpromising?
Define access through channels, responsibilities, and response arrangements. The phrase “direct access” is incomplete unless people know how to contact the practice, who initially receives the request, and when communication is reviewed. A portal message, scheduled call, and urgent clinical concern are not interchangeable situations.
Explain the process from the patient’s perspective. Is the first contact handled by a coordinator or clinician? Does a message start scheduling or request medical advice? What happens during staff absence? Which needs require an appointment? Those questions turn an abstract benefit into an operationally accurate description.
State after-hours arrangements carefully. A practice should describe its actual process and distinguish it from emergency care. Do not publish same-day appointments, continuous physician availability, or a guaranteed response time merely because such promises appear on a competitor’s website. Confirm the service capacity and any relevant conditions before using the claim.
Keep access information consistent across the website, printed materials, welcome messages, and agreements. If a program changes, update all affected explanations. A prospective patient may enter through a blog or social post rather than the main service page, so important limitations should not depend on finding a distant disclaimer.
Access can be valuable without being unlimited. Explaining how the team manages requests responsibly can help patients understand what the service supports. A clear process also gives staff a consistent answer when someone asks whether their concern fits the available service.
The concierge care marketing playbook at a glance
The four communication priorities below connect the service model with a patient’s decision: explain the offer, clarify costs, define access, and support informed choice. They apply to the information a practice shares, not to a promise of medical superiority.
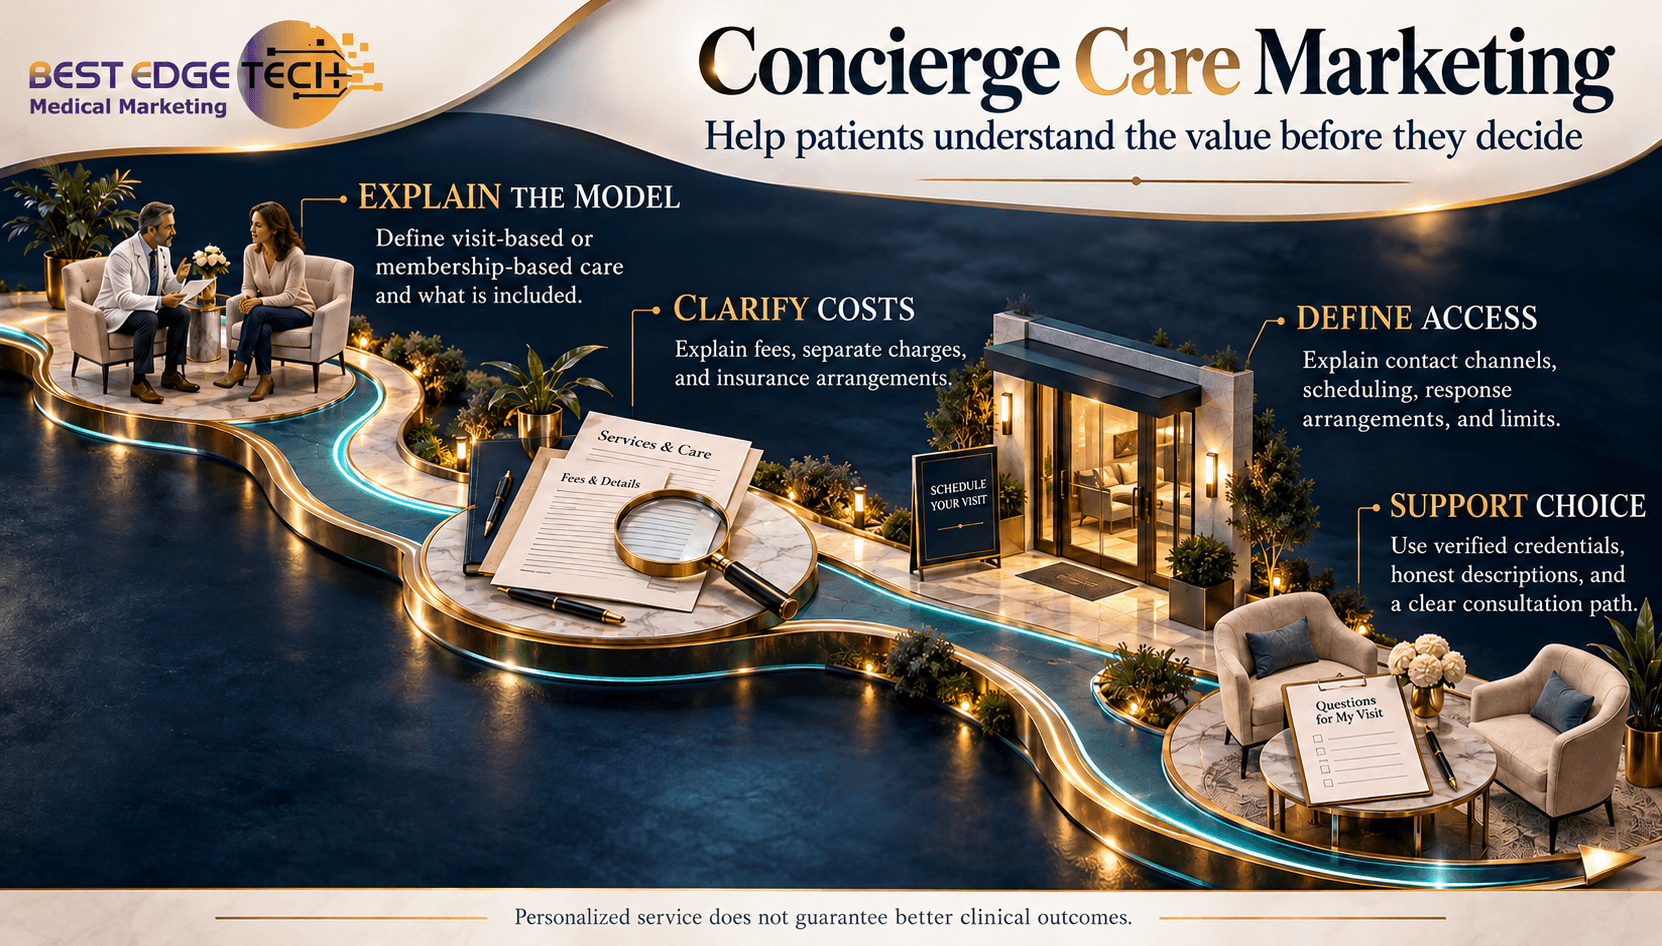
Use these priorities as a shared reference for the practice owner, clinical team, billing staff, and marketer. Each contributes facts that the others should not invent. The website becomes more useful when the service explanation, cost discussion, and inquiry process agree.
What should a concierge or cash-pay practice website include?
The website should give visitors a clear service explanation, verifiable provider information, and an understandable next step. Visual quality matters, but navigation and wording should make the decision easier. A visitor should be able to find the offer, its boundaries, and contact options without opening several unrelated pages.
Give each page a distinct responsibility
A main service-model page explains the arrangement. Specific service pages describe what is actually offered. Provider profiles establish identity and roles. A location page helps someone plan a real visit. Educational articles answer narrower questions and point back to the appropriate service information. Repeating the same membership pitch on every page can dilute useful distinctions.
What is the arrangement?
Define the model, payment basis, included scope, exclusions, and relevant agreement information.
Who provides it, and where?
Show verified clinician roles, actual offices, visit arrangements, and accurate access information.
What happens after contact?
Explain whether the next step is an inquiry, service-model discussion, clinical evaluation, or enrollment process.
Keep the pricing explanation close to the relevant offer. A call to action should not force someone into a sales conversation simply to discover whether a membership fee exists. When costs require individualized clarification, make that process visible and distinguish it from a treatment commitment.
Use realistic imagery without letting it imply unverified facilities, services, or staff. A conceptual illustration can explain a process; real provider and office information should use accurate representations. Identify actual locations in the text and avoid manufacturing a branch presence through generic photographs.
For broader usability and conversion structure, see medical website design that converts visitors into patients. The specific requirement here is that service-model and financial information remain as easy to find as the booking button.
How can concierge care marketing support search and AI discovery?
Organize content around real questions and the practice’s actual services. Clinic owners may search for concierge care marketing; prospective patients are more likely to ask about the care model, costs, insurance, location, or provider. Those audiences need different pages. This agency guide addresses marketing decisions rather than pretending to be a patient-facing clinic page.
Patient questions can guide educational content: what a membership includes, whether insurance is still billed, how consultation works, and what happens outside normal availability. Verify local search intent before selecting a primary phrase. Do not use “concierge doctor” to describe a service that the practice does not provide or a professional role that is inaccurate.
For local discovery, use truthful business information and real location details. Google’s business representation guidelines require accurate identities and locations. Community-focused content should explain practical access; adding affluent town names to interchangeable pages does not create a meaningful patient resource.
Direct answers, clear definitions, and relevant sources can make a page easier to understand and reference. Google’s AI-feature guidance says foundational SEO remains relevant and no special AI-specific markup is required. Keep important details in visible text and ensure any schema matches them. Neither content formatting nor structured data guarantees rankings or AI citations.
Support the commercial service pages through relevant internal links instead of duplicating them. Best Edge Medical Marketing’s medical SEO services provide a broader service context; this article concentrates on communicating personalized cash-pay value. Referral introductions, community education, and appropriate advertising can complement that content when their messaging remains accurate.
Which claims and trust signals need special care?
Separate verified service features from claims about clinical results. Appointment arrangements, coordination, and amenities should not be framed as proof of better diagnosis or treatment. The AMA’s ethics guidance on retainer practices calls for clear terms and transparent billing. Marketing should preserve the distinction between the service arrangement and clinical care.
A promise can be misleading through its overall impression, even if a small disclaimer appears elsewhere. The FTC’s health-products guidance addresses truthful, supported health claims. Review headlines, images, testimonials, and comparisons together. General enthusiasm about personalization does not substantiate a claim that outcomes improve for every patient.
Use provider credentials accurately. Name the professional role, verify relevant qualifications, and avoid implying a board certification or specialty that is not held. Attribute a medical review only when the identified person actually reviewed the material. A premium visual design is not a substitute for a verifiable clinical identity.
Reviews should reflect genuine experiences and be handled with privacy in mind. Do not invent patient stories, suppress feedback deceptively, or publish unsupported outcome claims through testimonials. Consult the FTC’s review-rule guidance and relevant platform policies. For a fuller workflow, see online reputation management for doctors.
Personalized service does not guarantee better clinical outcomes. This limitation should shape the primary message, not function as fine print beneath an incompatible headline. The same principle applies when a practice offers functional, longevity, or other cash-pay services: each clinical statement needs its own appropriate basis.
What should happen between an interested visitor and a consultation?
Use a clear, voluntary sequence that answers service questions before asking for a commitment. The process should identify what the person wants to understand, explain the relevant next step, and allow clinical suitability to be assessed through the appropriate professional route. A marketing form cannot determine whether treatment is indicated.
Present service scope, access arrangements, and the payment model.
Offer an appropriate route for questions about services, fees, and appointments.
Clarify its purpose, any fee, and what the person should expect.
Keep enrollment and clinical treatment decisions distinct and voluntary.
Make the call to action match the process. An inquiry button, introductory discussion, and clinical consultation should not all be labeled “start treatment.” Explain whether contact creates an appointment request, whether staff confirms it, and whether an evaluation is required before care proceeds.
Collect only information appropriate to the initial purpose through approved systems. Avoid asking visitors to place detailed medical histories into an ordinary marketing form. Review analytics, contact tools, and vendor arrangements before collecting or transmitting sensitive information. HHS tracking guidance discusses disclosures involving protected health information and notes a court limitation affecting part of its public-webpage guidance; applicability is fact-specific.
Staff should confirm understanding rather than rush the person through a script. If the inquiry concerns a service the practice does not offer, provide an accurate explanation instead of redirecting the person into an unrelated package. Clear qualification supports appropriate access and more useful marketing measurement.
How should a practice introduce a cash-pay or membership change?
Explain the change before promoting its benefits, and distinguish existing patients from new inquiries. A person who already receives care may need to understand whether fees, appointment arrangements, or continuity will change. Their questions are different from those of someone discovering the practice for the first time.
Prepare a plain-language explanation covering what changes, what stays available, which services are included, how costs work, and whom to contact with questions. Verify the actual timetable and agreements before publication. Avoid vague pressure about a closing enrollment window or limited places unless the claim accurately reflects the program.
Use consistent information in letters, website pages, staff conversations, and appointment materials. A transition creates confusion when a patient receives a reassuring email but encounters different conditions during scheduling. Staff preparation should therefore precede a major campaign.
For retainer transitions, the practice’s clinical and legal advisers should review continuity and patient-choice obligations. A marketing team should not decide how an existing care relationship may end. Provide a respectful route for questions and alternatives consistent with the practice’s responsibilities, rather than presenting enrollment as the only acceptable decision.
Keep treatment promotion separate from model education. A new payment arrangement does not establish that a patient needs additional tests, procedures, or recurring treatment. The decision to enroll in a service model and the decision to receive a specific intervention require different explanations.
How should concierge care marketing performance be measured?
Measure informed inquiries and operational follow-through alongside visibility. Traffic, contact requests, consultations, and memberships describe different stages. A large volume of confused or irrelevant requests can indicate a messaging problem rather than a successful campaign.
| Stage | What to review | What it does not prove |
|---|---|---|
| Discovery | Relevant queries and visits to the service-model pages. | Clinical need or willingness to enroll. |
| Understanding | Recurring questions and clarity of service, cost, and access explanations. | A medical recommendation or informed consent to treatment. |
| Inquiry | Appropriate requests, completed contact processes, and response handling. | An attended appointment or completed enrollment. |
| Operations | Consultation attendance and accurate explanations recorded in approved systems. | Guaranteed clinical results or future retention. |
Establish a baseline and record meaningful page or process changes. Review why people ask questions, whether the same misunderstanding repeats, and whether staff can handle the actual demand. Do not claim that a layout change caused every later enrollment when campaigns, capacity, seasonality, or other factors also changed.
Use privacy-reviewed reporting. Keep patient details and treatment information out of ordinary marketing dashboards and avoid exporting clinical notes to advertising platforms. Aggregated operational observations can help refine the explanation without turning healthcare inquiries into an unrestricted data source.
There is no universal conversion rate or dependable ranking timetable for this offer. A useful improvement may be fewer misunderstandings, clearer cost discussions, or more appropriately directed consultation requests. Define success with the practice before interpreting the numbers.
What should a practical implementation plan include?
Start with accurate service information, then build the website explanation and inquiry process around it. The following sequence is an editorial work plan, not a promise of visibility or enrollment gains within a fixed period.
- Document the offer. Verify the model, services, provider roles, fees, exclusions, and actual insurance relationship with the appropriate practice team.
- Audit existing explanations. Compare pages, agreements, printed materials, and staff scripts. Resolve contradictions and unnecessary page overlap.
- Build the primary page. Give the service model a clear destination, useful supporting pages, accurate provider information, and a straightforward inquiry route.
- Prepare operations. Confirm who answers questions, how requests are handled, and how the next appointment is described.
- Publish, inspect, and improve. Test mobile readability, contact functions, image delivery, indexing settings, and later schema consistency. Review real questions after launch.
Assign ownership for each fact. Clinical staff verifies clinical scope; billing verifies financial explanations; operations confirms access; marketing organizes the communication. If the offer changes, update the information across channels rather than allowing a former promise to remain in a campaign.
Paid advertising, referrals, and educational events can support the plan when appropriate, but they should lead to the same accurate explanation. A campaign cannot repair an undefined service or a misleading agreement. Prioritize the information patients need to decide and the process the team can reliably deliver.
Make the value understandable before asking patients to commit
Concierge care marketing works as a communication system: the service explanation, costs, access arrangements, provider information, and inquiry route reinforce one another. A distinctive visual identity helps present that information, but the substance must come from the practice’s real offer.
Best Edge Medical Marketing is based in Raleigh and serves healthcare organizations across the United States. Its medical website design services, SEO services, and anti-aging medical practice marketing provide relevant starting points for discussing how personalized cash-pay services are explained online. Scope should follow a review of the actual practice and existing content.
Build a clearer service-value story
Bring your website, service model, fee structure, and consultation process. Discuss how your pages can make personalized care easier to understand and help prospective patients reach an appropriate next step.
Frequently asked questions about concierge care marketing
What is concierge care marketing?
Concierge care marketing explains a practice’s personalized service model, included services, fees, access arrangements, and inquiry process. It can support a formal membership or another cash-pay arrangement, depending on what the practice actually offers. The objective is informed understanding and appropriate inquiries. The term should not imply unlimited availability, insurance coverage, or better clinical outcomes simply because the service is described as personalized.
Is concierge-level care always membership-based?
No. Concierge-level care may describe an attentive service experience without a recurring membership. A formal concierge arrangement may involve a retainer, while other practices charge for visits or particular services. The website should identify the actual payment model and included scope. Patients should not have to infer whether they are paying for a single evaluation, an ongoing agreement, or services billed separately.
How is direct primary care different from concierge medicine?
Direct primary care generally uses periodic direct payments for a defined primary care scope, typically replacing third-party billing for those contracted services. Concierge arrangements can have different membership benefits and separate insurance billing. Labels alone do not establish the terms. Explain the actual contract, included services, exclusions, and relationship to other healthcare costs rather than treating all personalized or membership-based practices as identical.
Should a practice publish its fees online?
A practice should make the payment structure understandable and provide a clear route to current cost information. Explain required fees, recurring charges, included services, and important exclusions. When costs depend on an evaluation, describe how the patient receives relevant information before agreeing. A general price page does not automatically replace an estimate required for a particular service or establish what an individual insurance plan covers.
Does insurance cover concierge membership fees?
Coverage depends on the specific arrangement and payer. Medicare states that it does not cover concierge membership fees, while separate medical services may be subject to applicable Medicare rules. Do not assume the same answer for every plan or service. The practice should explain its actual insurance relationship and direct patients to the appropriate billing or coverage contact without guaranteeing reimbursement or presenting a membership as comprehensive insurance.
Can concierge marketing promise same-day or continuous access?
Only describe access arrangements that the practice can accurately support, including their conditions and limits. Explain how requests are received, who responds, when communication is reviewed, and how after-hours concerns are handled. A contact channel does not automatically mean continuous physician availability or emergency care. Avoid adopting a competitor’s access claim without verifying your practice’s actual operations and relevant professional requirements.
Does personalized cash-pay care guarantee better medical outcomes?
No. A personalized service experience does not establish that diagnosis, treatment, or outcomes will be superior for an individual patient. Distinguish verified service features from clinical effectiveness claims, which require appropriate evidence and qualified review. Marketing should explain the actual offer and its boundaries. A membership fee or premium description should not be presented as proof that a particular intervention is suitable or will succeed.
What should the main service page include?
The main page should define the care model, who provides services, what is included, which charges may be separate, and how access works. Add verified provider information, actual visit arrangements, and a clear inquiry route. Explain whether the next step is a service-model discussion, clinical evaluation, or enrollment process. Supporting pages should answer distinct questions rather than repeat the same promotional message across the website.
How can a practice measure marketing quality beyond traffic?
Review whether visitors reach the appropriate information, whether recurring questions reveal confusion, and whether completed inquiries fit the actual service. Track response handling and consultation attendance through approved systems, keeping those stages separate from enrollment and treatment. Avoid placing patient details in ordinary marketing analytics. A clear baseline and a record of changes help the team interpret performance without attributing every result to one campaign.
How can Best Edge Medical Marketing support a cash-pay practice?
Best Edge Medical Marketing offers healthcare marketing, SEO, and website design services. A practice can discuss how its pages communicate service scope, costs, access, provider information, and the consultation process. The agency is based in Raleigh and serves healthcare organizations nationally. Recommendations should follow a review of the practice’s actual offer and existing content, with clinical, billing, and compliance facts verified by the appropriate professionals.
Sources and editorial standards
Sources and policy information checked October 14, 2026. Care agreements, insurance arrangements, and applicable requirements vary. This article provides marketing education, not an individualized clinical, billing, or legal determination. Its messaging examples and implementation sequence are editorial recommendations, not measured conversion forecasts.
- American Medical Association: Retainer practices
- American Academy of Family Physicians: Direct primary care
- Medicare: Concierge care coverage
- CMS: Good faith estimates
- Federal Trade Commission: Health Products Compliance Guidance
- Federal Trade Commission: Consumer reviews and testimonials rule guidance
- Google: Guidelines for representing your business
- Google Search Central: AI features and your website
- HHS: Online tracking technologies guidance
Best Edge Medical Marketing staff: editorial responsibility
Published by Best Edge Medical Marketing. The guide draws on public professional, agency, and search-platform resources to explain responsible healthcare marketing. A treating practice’s clinical statements, fees, insurance information, and service commitments should be verified by its appropriate clinical and operational professionals.